
On-Premises AI for Healthcare: An Ollama Blueprint

CTO & Co-Founder
CTO & Co-Founder at Nirmitee.io. Architects healthcare integrations across FHIR, SMART on FHIR, ABDM and NHCX, writing from production experience taking hospital software from sandbox to go-live.
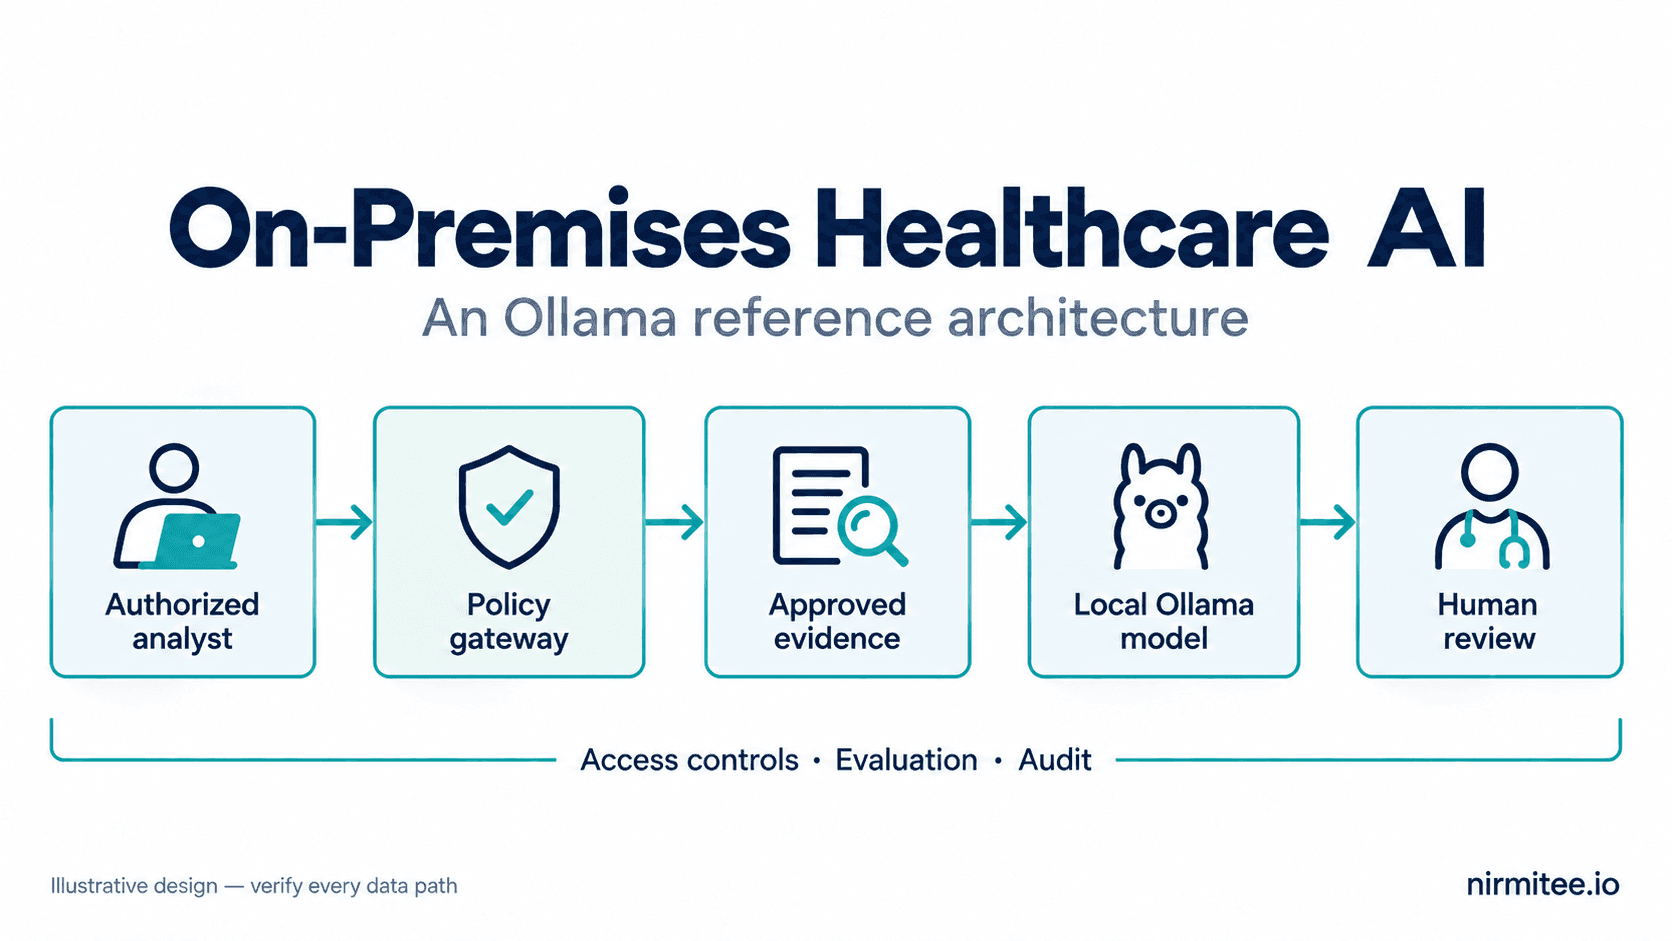
On-premises AI for healthcare means operating the model and its supporting workflow inside an explicitly controlled environment. Ollama can provide local model serving. The application still needs authentication, authorized data access, evaluation, audit controls and an operating team.
Start with a practical insurance-operations question: “Why did this batch of claim records fail validation, and which source evidence should an analyst inspect?”
A useful assistant retrieves the relevant records, explains the validation results and points to the evidence. It should not invent a reason for denial or change a member's coverage. That narrower task makes the required data, permissions and acceptance tests much easier to define.
The workflow below is a proposed healthcare application of enterprise data and local-model engineering. It is not a claim that a particular insurer has deployed it.
For implementation planning, our healthcare AI service can scope a bounded workflow around the data and controls it requires.
Put the assistant behind an authorized data interface
The tempting shortcut is to connect a local model directly to a database and let it generate queries. That leaves important questions unanswered: which records may this user see, how much data may a query return, and what happens if a document contains instructions aimed at the model?
Use an application boundary that enforces those decisions before data reaches the prompt.
| Architecture stage | Responsibility |
|---|---|
| Authorized analyst → authenticated application | Establish identity and the requested workflow. |
| Policy and tool gateway → approved data views | Enforce permissions, narrow tools and result limits in code. |
| Bounded evidence context → local Ollama model | Supply only the evidence authorized for the request. |
| Output checks and evidence references → human review | Check support for answers and keep consequential decisions with authorized people. |
| Audit events and evaluation across gateway and outputs | Verify access boundaries, evidence quality and behavior after changes. |
This is a reference design. Select the actual components after agreeing the workflow and security boundary.
Expose narrow operations such as retrieving a batch summary, looking up a validation rule or reading an approved source record. Enforce permissions and result limits in code. A model instruction asking it to “only use authorized data” is not an access-control mechanism.
Begin with read-only tools. If a later workflow proposes writes, keep authorization, validation and approval outside the model's discretion.
Running models on your own hardware often goes with adapting a small open model to one task. Our guide to fine-tuning LLMs on clinical notes covers de-identification, patient-level splits and QLoRA on a single GPU.
Trace the whole data path, not just inference
The model may run locally while another component sends data elsewhere. Document every dependency: OCR, embedding generation, vector storage, tracing, crash reporting, backups, support access and model downloads.
Ollama distinguishes local and cloud-hosted models. Its documentation provides a local-only configuration that disables cloud features, and explains its default loopback binding. Verify the installed version and effective configuration rather than assuming that the product name proves isolation. Ollama FAQ
A local model does not itself establish HIPAA compliance. Cloud services can also be used within an appropriate HIPAA arrangement; HHS guidance addresses safeguards and business associate agreements for cloud providers handling ePHI. Deployment location is one part of the design and risk assessment. HHS cloud-computing guidance
For an on-premises design, test the actual egress paths. Include model provisioning and updates in the operating plan, so an offline runtime does not depend on an undocumented live download.
Use transaction engineering to prepare evidence
Transaction throughput and model throughput are different workloads.
The data platform can ingest and validate records in batches or streams using deterministic transformations. The assistant should consume a limited, authorized evidence set for a particular question. Sending every transaction through an LLM adds another expensive and difficult-to-validate processing stage without necessarily improving the result.
For claims operations, a useful separation is:
| Responsibility | Preferred starting point |
|---|---|
| Parse identifiers, amounts and timestamps | Deterministic code with source-specific validation |
| Match records and detect duplicates | Explicit keys, version policy and reconciliation rules |
| Compute batch counts and control totals | Tested data transformations |
| Explain a known validation exception | Assistant using the rule, record and source evidence |
| Approve a correction or consequential action | Authorized human workflow |
This is where data engineering supports AI. The healthcare data engineering service focuses on the source contracts, quality checks and ownership that make those evidence views dependable.
Size the workload before choosing the GPU
Avoid a universal promise such as “local inference is faster” or “self-hosting becomes cheaper at a fixed number of calls.” The answer changes with the model, precision, context length, output length, concurrency and operating requirements.
Build a representative request set: short explanations, long supporting documents, unanswered questions and concurrent analyst sessions. Measure time to first token, complete-response latency, memory use, queue time and failure rate under that workload.
Keep data-pipeline throughput separate from inference measurements. A system handling many transactions does not establish that the model can answer many simultaneous questions. Report those capacities independently.
Compare the options using the same workload and quality threshold. Include hardware, utilization, redundancy, updates and engineering support when estimating self-hosted cost. Include applicable service and data-handling arrangements when evaluating a hosted alternative.
Make “I cannot establish that” an accepted answer
A synthetic review question might ask: “Did the corrected record reach the reporting dataset?” If the available evidence contains the original record but no downstream acceptance event, the assistant should identify that gap. It should not infer success from an unrelated completed job.
Create an evaluation set with expected evidence and acceptable answers. Include wrong or missing policy versions, conflicting documents, unavailable records, permission-denied queries and questions that cannot be answered from the supplied context.
Measure whether answers are supported, whether references point to the right evidence, whether the model abstains appropriately, and whether it remains within authorized data. Readability is useful, but a fluent unsupported answer is still a failed test.
Our healthcare LLM evaluation guide explains how to structure that verification work.
Operate the assistant as a service
Pin and record model and application versions. Keep a rollback path. Define who responds when the model is unavailable, a retrieval index is stale or a tool returns an unexpected schema.
Log the events needed to investigate behavior without indiscriminately duplicating sensitive documents into application logs. Establish retention and access policies for prompts, responses and retrieved evidence. Verify that deletion and permission changes propagate to supporting stores.
Run the same evaluation set before and after changes to the model, prompt, retrieval logic or data mapping. A model upgrade can change tool behavior even when the application code is unchanged.
These responsibilities are a better starting point for deployment planning than a catalogue of model names. The bounded-autonomy architecture guide develops the control boundaries further.
Start with one analyst task and a readiness review
Choose one workflow with a named owner, available evidence and a clear decision about what the assistant may do. A claims-data exception explainer is a more bounded first engagement than “automate insurance with AI.”
Bring the current data flow, intended users, hosting constraints and representative questions. The review should produce an access-boundary diagram, a workload-sizing plan, an evaluation set and a scoped implementation proposal.
Discuss a healthcare AI readiness review.
Talk to our team about the analyst task, hosting boundary and evidence your first healthcare AI workflow will need.
Ready to scale?
Talk to our healthcare engineering team about building, integrating, and shipping faster.
Frequently Asked Questions
Can Ollama be used for on-premises healthcare AI?
Does running a model locally make it HIPAA compliant?
Should every insurance transaction pass through an LLM?