Why Claims Get Denied Before They Are Even Sent

CTO & Co-Founder
CTO & Co-Founder at Nirmitee.io. Architects healthcare integrations across FHIR, SMART on FHIR, ABDM and NHCX, writing from production experience taking hospital software from sandbox to go-live.
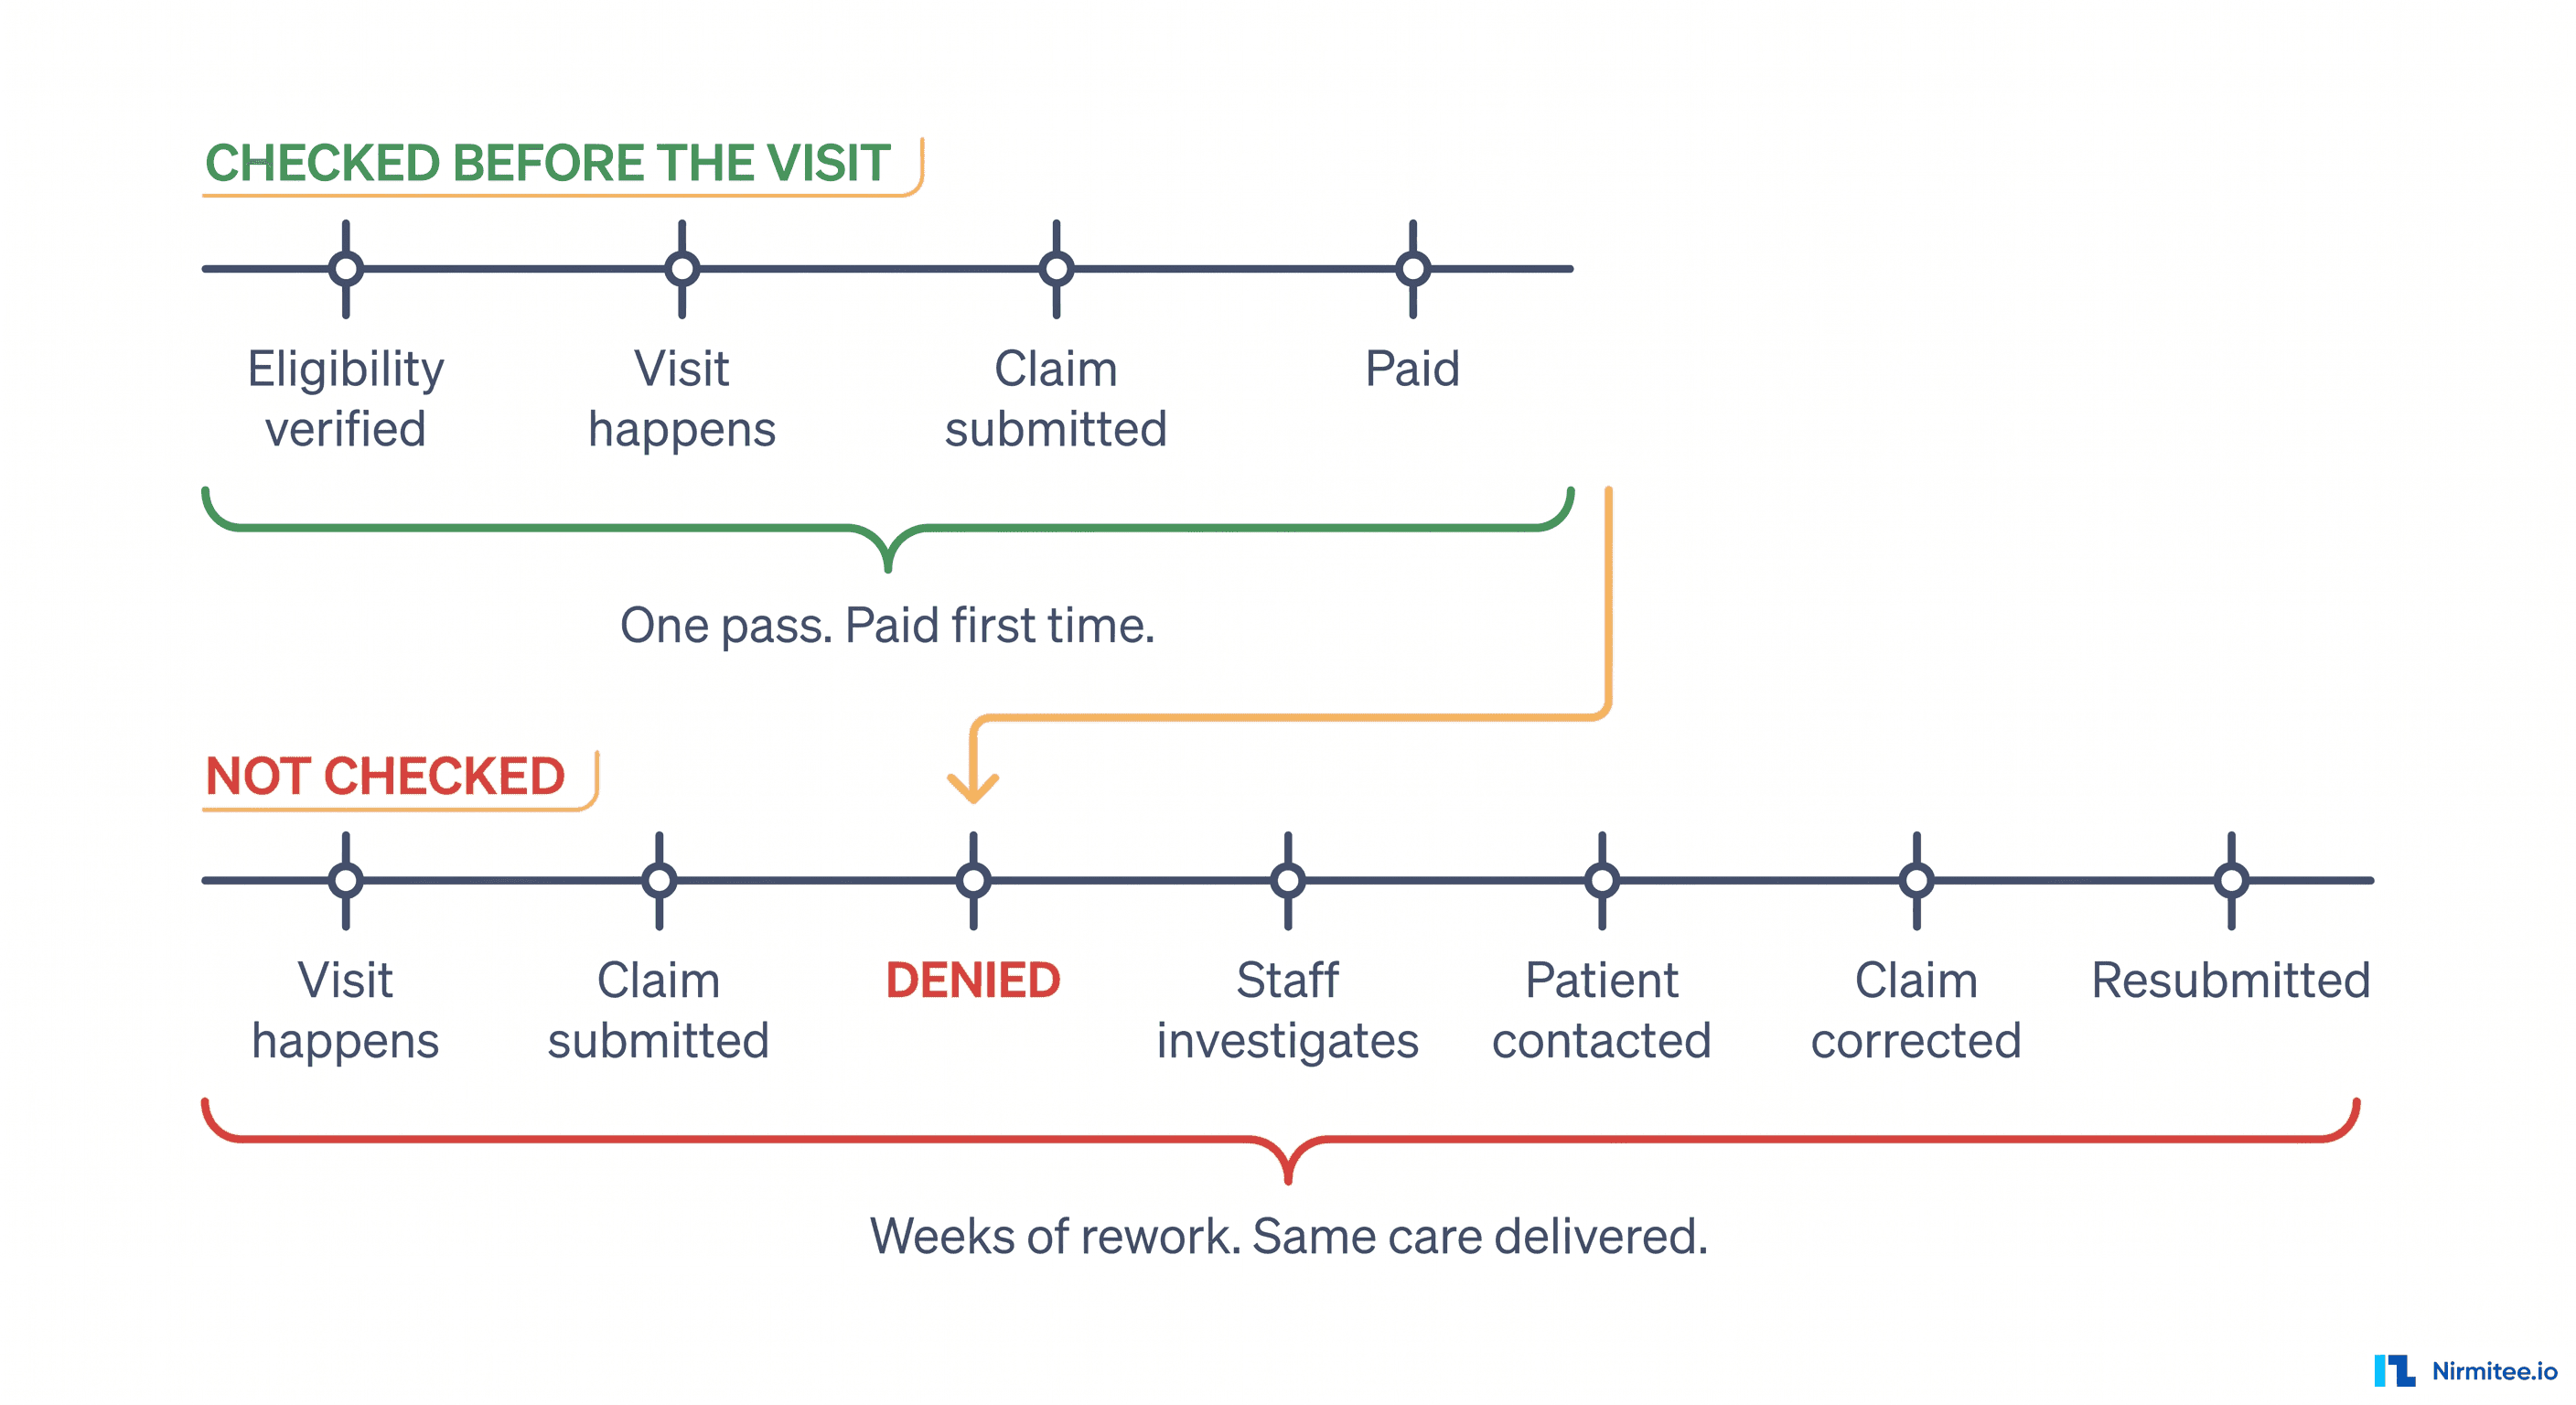
Every denied claim is work done twice. The care was delivered, the note was written, the claim was built and sent, and then an insurer said no, and the whole thing starts again with a staff member on the phone.
What makes this frustrating is that a large share of denials were entirely predictable before the patient walked in. The coverage had ended. The plan had changed. The member ID was wrong. Nobody asked.
Related: see how we approach this in our RCM software development.
The cheapest thing in the revenue cycle
Checking whether a patient's insurance is active costs a fraction of a cent and takes seconds. It happens electronically, in the background, and needs nobody's attention when the answer is good.
Compare that with what happens when the check is skipped, and the claim is denied:
- A staff member investigates why
- Someone contacts the patient for current insurance
- The claim is corrected and resubmitted
- The clock restarts — another few weeks before payment
- Sometimes the patient is unreachable and the balance is written off entirely
Industry estimates for reworking a single denied claim generally run to around $25 in staff time. The check that would have prevented it costs almost nothing. That ratio is the entire argument, and it is why eligibility is the first thing experienced revenue cycle teams automate.
Why it gets skipped
Not carelessness. Almost always one of three design failures:
It is a manual screen. Someone has to remember to open it, on a busy day, for every patient. Anything that depends on remembering fails at exactly the moments it matters most.
It was checked once, at registration. A patient registered in March with active coverage may have changed jobs in June. Verification is treated as an onboarding step rather than an ongoing fact, and coverage changes without telling anyone.
The answer is not connected to anything. The system knows the coverage expired and still generates the claim, because the eligibility record and the billing process do not talk. This is the most expensive of the three, because it produces denials the system had the information to prevent.
Coverage ends on a date you already know
Most plans have a termination date, and it is usually visible in the eligibility response months in advance. That makes expiry one of the few genuinely predictable problems in healthcare billing.
Handled well, it looks like this:
- A month out, billing staff see it and have time to resolve it calmly
- A week out, the patient is asked for updated insurance before their next appointment
- Once expired, the system stops generating insurance claims for that patient and prompts a self-pay conversation instead
That third step is where most platforms fall down. An expired policy that still auto-generates a claim produces a guaranteed denial — the system spends a full claim cycle discovering something it already knew.
Telling patients what they owe, before
Good eligibility data enables the single biggest lever on patient collections: telling someone what a visit will cost before they have it.
The response usually includes copay, coinsurance and — importantly — remaining deductible. That is enough to estimate the patient's share with reasonable confidence.
Why it matters commercially: collection rates fall steeply once a patient leaves. Collecting at the point of service is dramatically more effective than invoicing later, and you can only collect at the point of service if you know the amount at the point of service.
It is also simply better care. Nobody enjoys an unexpected bill weeks after a therapy session, and surprise balances are a common reason patients disengage from treatment.
One caution: always present it as an estimate. Deductible figures lag — other claims may be in flight. Quoting an exact figure that later changes damages trust more than an honest estimate would.
What good looks like
Four questions tell you whether eligibility is working. If nobody can answer them, that is the finding:
- What share of upcoming appointments have verified coverage? This should be close to all of them, automatically.
- What share of denials are eligibility-related? If it is meaningful, this is the cheapest problem you have to fix.
- How much patient responsibility is collected at the visit versus billed afterwards?
- How many patients are seen on coverage that has already expired? This should be approaching zero and rarely is.
Questions worth asking your team
- Does eligibility run automatically before appointments, or does someone have to remember?
- How often is coverage rechecked for an existing patient?
- If coverage has expired, can the system still generate an insurance claim?
- Can we tell a patient what they will owe before their visit?
- What share of our denials would a pre-visit check have prevented?
The third question is the sharpest. If the answer is yes, you are manufacturing denials you already had the data to avoid.
Many preventable rejections can be caught inside the product before submission. Our guide to claim scrubber software shows how, and rendering vs billing provider covers the provider identity errors behind a large share of them.
The short version
Eligibility verification is the highest-return, lowest-cost automation in the revenue cycle. It prevents denials rather than working them, enables collection at the point of service, and removes a common cause of patient frustration.
It only works if it runs on a schedule rather than on memory, if the answer is connected to claim generation, and if coverage expiry is treated as the predictable event it is.
If denials are already a problem, our piece on the real cost of getting claims integration wrong covers where else revenue leaks between care delivered and cash received.
Ready to scale?
Talk to our healthcare engineering team about building, integrating, and shipping faster.
Frequently Asked Questions
What share of claim denials are preventable?
Why is eligibility checking skipped so often?
What does it cost to rework a denied claim?
How should coverage expiry be handled?
Why does collecting at the point of service matter so much?