Checked against CMS ACCESS documents on Nov 22, 2026. The documents are listed under Sources at the end of this page.
Readiness score
Score your CMS ACCESS model readiness in seven questions
Answer each question 0 (not started), 1 (partly in place or manual) or 2 (automated and tested). The total out of 14 places you in one of three bands. The questions and bands are Nirmitee's engineering judgment, not a CMS scale.
How the ACCESS model works: the flow every patient goes through
ACCESS pays Medicare Part B providers a monthly Outcome-Aligned Payment for technology-supported chronic care in Original Medicare, for 10 years: it started July 5, 2026 and runs to June 30, 2036 (model page, RFA). There are four tracks today (eCKM, CKM, MSK pain and behavioral health); tracks for heart failure, COPD, substance use disorder and tobacco cessation start April 1, 2027 (model page, technical FAQ). More than 160 organizations take part (participants page, updated Nov 3, 2026).
- 1. Eligibility API
Coverage check. Original Medicare only (RFA). - 2. Clinical check
Track criteria met and evidence stored. - 3. Alignment API
Alignment date starts the care period and billing (OAP billing guidelines). - 4. Care and data
Validated upper-arm BP cuff, labs, PHQ-9 (RFA, payment amounts document). - 5. Report
Baseline within 60 days of alignment, then quarterly, then end of period, through the FHIR Data Reporting API (payment amounts document, RFA). - 6. Bill and reconcile
Monthly G-code claim; the withheld 50% is reconciled after each 12-month care period (payment amounts document).
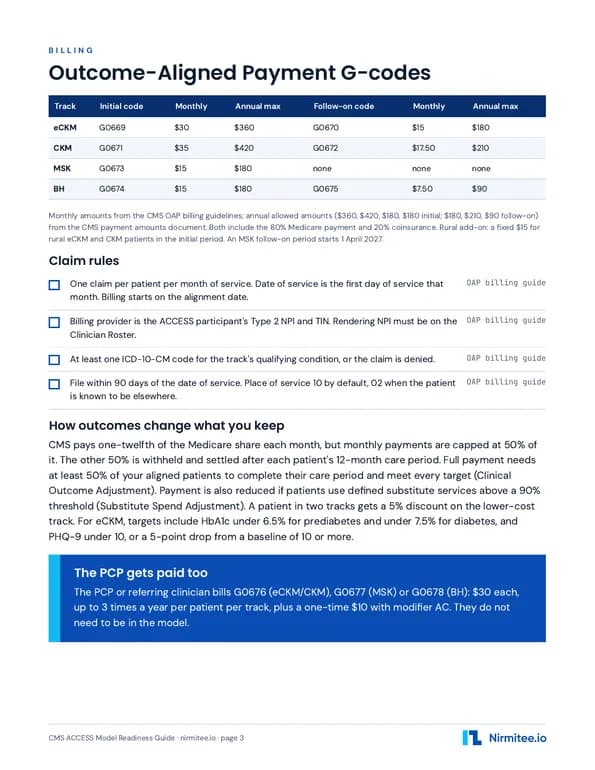
ACCESS model G-codes: Outcome-Aligned Payments by track
Each track has an initial-period code and, for most tracks, a lower follow-on code, paid monthly per aligned patient. Source: CMS ACCESS payment amounts and performance targets.
| Track | Initial code | Monthly | Annual max | Follow-on code | Monthly | Annual max |
|---|
| eCKM | G0669 | $30 | $360 | G0670 | $15 | $180 |
| CKM | G0671 | $35 | $420 | G0672 | $17.50 | $210 |
| MSK | G0673 | $15 | $180 | none | none | none |
| BH | G0674 | $15 | $180 | G0675 | $7.50 | $90 |
Allowed amounts include the 80% Medicare payment and 20% coinsurance, from the CMS ACCESS payment amounts document (v10), covering Jul 5, 2026 to Dec 31, 2027. Rural add-on: a fixed $15 for rural eCKM and CKM patients in the initial period (OAP billing guidelines). The MSK follow-on period starts April 1, 2027 (payment amounts document). Multi-track discount: when a patient is in more than one track with the same participant, CMS takes 5% off the lower-cost track(s) (payment amounts document).
Claim rules
- One claim per patient per month. The first date of service can be the first day of the care period, which is the date of alignment; it does not need to be the first of a calendar month.OAP billing guidelines
- Bill under the ACCESS participant's TIN. Rendering NPIs must be on the Clinician Roster before billing.OAP billing guidelines
- At least one ICD-10-CM code for the track's qualifying condition, or the claim is denied.OAP billing guidelines
- File within 90 days of the date of service, or the claim is not payable. Use place of service 10 by default when most services are asynchronous and received at home.OAP billing guidelines
How outcomes change what you keep. CMS pays one-twelfth of the Medicare share each month for valid monthly claims, capped at 50% of the Medicare portion. The other 50% is withheld and reconciled after each patient's 12-month care period through the Clinical Outcome Adjustment and the Substitute Spend Adjustment. Full payment needs at least 50% of aligned patients to complete the care period and meet all required targets (the Outcome Attainment Threshold); the Substitute Spend threshold is 90%. Targets include final HbA1c under 6.5% (prediabetes) or under 7.5% (diabetes), or a 1-point HbA1c reduction for diabetes, and PHQ-9 under 10 or a 5-point reduction from a baseline of 10 or more. Source: CMS ACCESS payment amounts and performance targets.
The PCP gets paid too. The PCP or referring clinician bills G0676 (eCKM/CKM), G0677 (MSK) or G0678 (BH): $30 each, up to 3 times per 12 months per patient per track, plus a one-time $10 with modifier AC (CMP billing guidance). They do not need to be in the model.
23 technical checks before you scale
Each check names its CMS source. Checks marked "Nirmitee recommendation, not a CMS requirement" are our engineering advice.
Enrollment and eligibility
- Organization enrolled in Medicare Part B, not as a DMEPOS or laboratory supplier.RFA
- Medicare-enrolled Medical Director designated.RFA
- Eligibility API integrated and called before every enrollment.RFA
- We recommend a local check that confirms Original Medicare coverage before enrollment and logs the result.Nirmitee recommendation, not a CMS requirement
- Clinical eligibility rules per track coded and the evidence stored.RFA
- Alignment and Unalignment API calls wired, with the alignment date stored as the first day of the care period.RFA, OAP billing guidelines
PCP attribution and communication
- We recommend capturing each patient's primary care or referring provider, with NPI, so updates can be sent.Nirmitee recommendation, not a CMS requirement
- We recommend validating the provider NPI against NPPES and storing an electronic address for updates.Nirmitee recommendation, not a CMS requirement
- Patient consent to share care updates with their Identified Care Team captured before the first update.RFA
- Electronic updates sent to the referring or primary care provider via an HIE or CMS Aligned Network at initiation, completion and clinical milestones.Technical FAQ
- We recommend delivery confirmation and retry for failed sends.Nirmitee recommendation, not a CMS requirement
Care delivery data capture
- Validated upper-arm BP cuff with timestamped, source-verifiable transmission; no manual entry.RFA
- We recommend ingesting lab results (HbA1c) with source and date.Nirmitee recommendation, not a CMS requirement
- PHQ-9 and other instruments captured with scores stored as coded data.CMS ACCESS payment amounts and performance targets
- We recommend tagging each data point with patient, track and measurement time.Nirmitee recommendation, not a CMS requirement
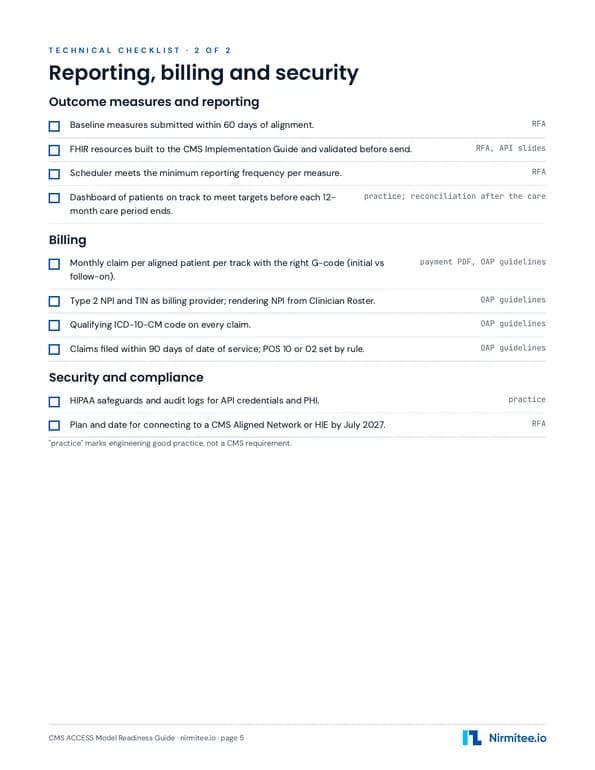
Outcome measures and reporting
- Baseline measures submitted within 60 days of alignment, or the patient is unaligned.CMS ACCESS payment amounts and performance targets
- Measures reported through the FHIR-based Data Reporting API.RFA
- Scheduler sends measures quarterly and at end of period, after the baseline.CMS ACCESS payment amounts and performance targets
- We recommend a dashboard of patients on track to meet targets before each care period ends.Nirmitee recommendation, not a CMS requirement
Billing
- Monthly claim per aligned patient per track with the right G-code (initial or follow-on).CMS ACCESS payment amounts and performance targets; OAP billing guidelines
- Participant TIN as billing provider; rendering NPI on the Clinician Roster.OAP billing guidelines
- Qualifying ICD-10-CM code on every claim.OAP billing guidelines
- Claims filed within 90 days of the date of service; POS 10 as the default when most services are asynchronous at home.OAP billing guidelines
Security and compliance
- We recommend HIPAA safeguards and audit logs for API credentials and PHI.Nirmitee recommendation, not a CMS requirement
When you want it done for you
ACCESS Operations Build
We integrate the four CMS APIs, PCP lookup and care updates, and a monthly claim and outcome dashboard into your platform, starting with a readiness review of your current setup.
The four CMS APIs: Eligibility API, Alignment API, Unalignment API and the FHIR Data Reporting API.
Integrations we have delivered: athenahealth, eClinicalWorks, and an Epic SMART on FHIR patient-facing app.
You own the code: everything we build lives in your repositories.
Price: fixed-scope quote after a scoping call.
The call: a 30-minute technical review with a Nirmitee engineer, not a sales pitch. No patient data needed.
Book an ACCESS readiness call